
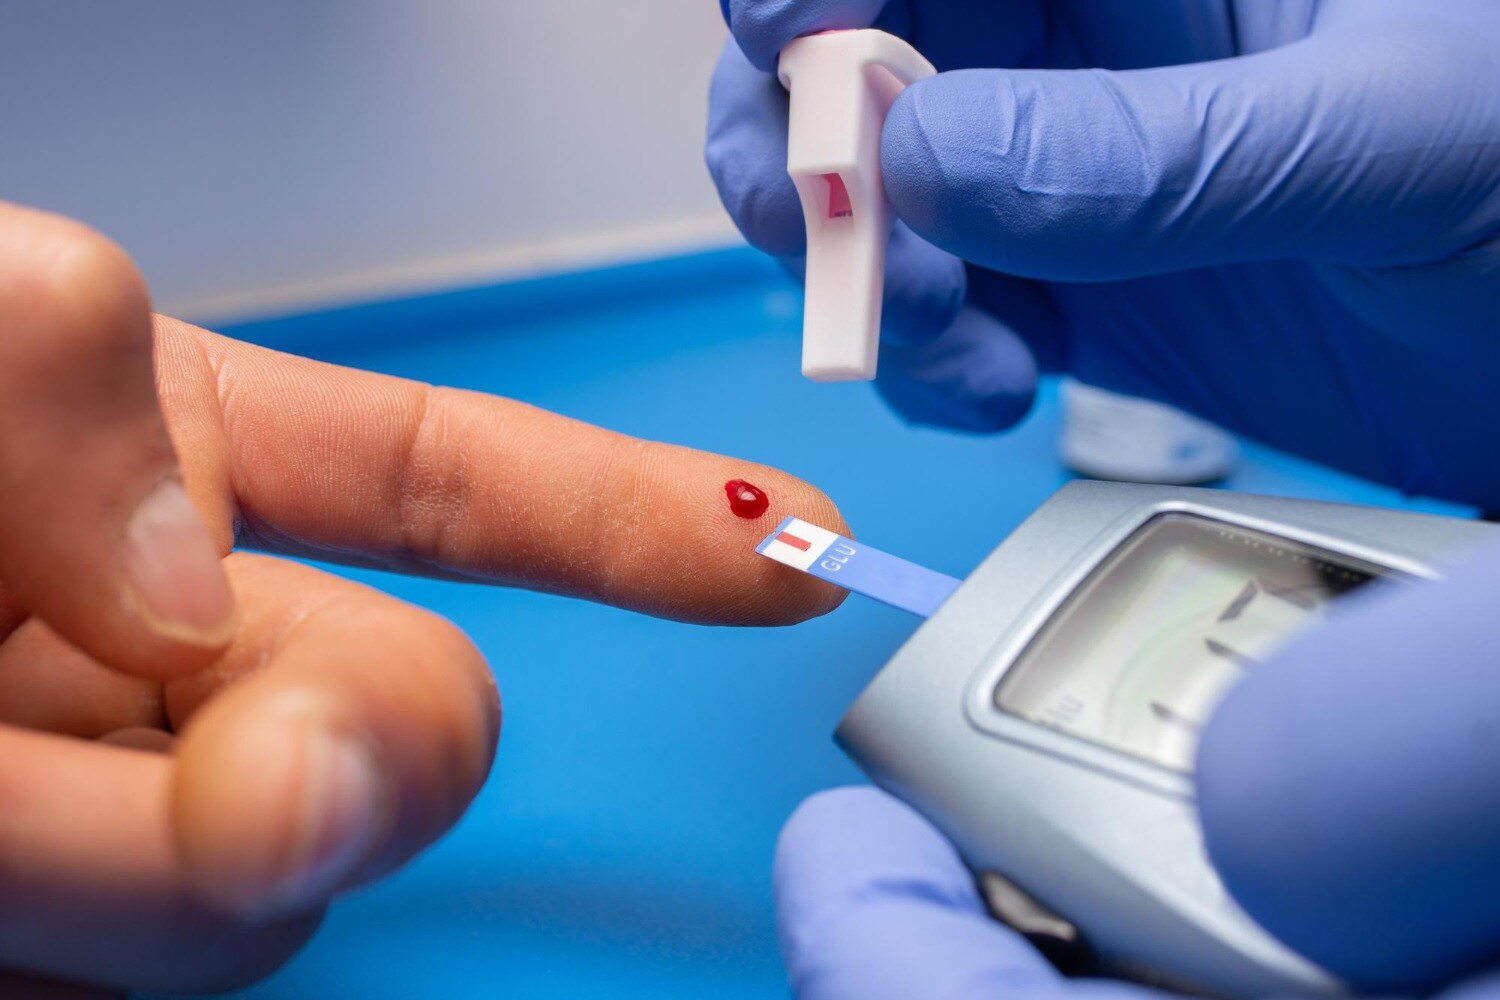
High glucose does not always mean the same condition, and the right next step depends on your symptoms, readings, medicines, pregnancy status and risk of complications. By the end, you will know when to seek routine diabetes care, what to take to the appointment, how to prepare, and when emergency treatment is safer than waiting.
Key takeaways
- Seek emergency care for severe low sugar, confusion, vomiting, or breathing difficulty.
- Bring glucose readings, medicines, insulin doses, laboratory reports, and your questions.
- Track HbA1c, fasting glucose, post-meal glucose, blood pressure, kidney function, and cholesterol.
- Ask about monitoring, meal planning, exercise, insulin technique, and complication screening.
When should you see a diabetologist, physician, endocrinologist or emergency team?
Choose care by severity and diagnostic uncertainty. A general physician can assess an initial abnormal reading, common type 2 diabetes and routine follow-up. A diabetologist can manage glucose patterns, insulin, hypoglycemia and diabetes complications.
An endocrinologist is useful when diabetes type is unclear, glucose remains difficult to control, or thyroid and other hormone disorders are involved.
| Provider | Best fit | Escalate when |
|---|---|---|
| General physician | Initial abnormal result, likely type 2 diabetes, routine review | Readings remain uncontrolled or complications appear |
| Diabetologist | Glucose patterns, insulin, hypoglycemia, diabetes complications | Rapid weight loss, ketones or early insulin need raises diagnostic doubt |
| Endocrinologist | Unclear type, thyroid or hormone disorder, difficult control | Consider type 1, latent autoimmune, pancreatic or secondary diabetes |
| Emergency team | Acute severe symptoms or dangerous glucose levels | Do not wait for a scheduled appointment |
Laboratory diabetes thresholds are HbA1c 6.5% or higher, fasting plasma glucose 126 mg/dL or higher, 2-hour glucose 200 mg/dL or higher after a 75-g oral glucose-tolerance test, or random glucose 200 mg/dL or higher with classic symptoms or hyperglycemic crisis. Without unequivocal hyperglycemia, confirmation is usually needed.
Seek emergency care for vomiting, abdominal pain, deep or rapid breathing, dehydration, severe drowsiness, confusion, fruity breath, or very high glucose with ketones. Severe hypoglycemia with confusion, seizure, unconsciousness or inability to swallow is also an emergency. A new foot ulcer, spreading redness, black tissue, fever, or a cold, pale foot needs urgent assessment.
A diabetes specialist in Nashik can help when routine care no longer fits.
How do you book a diabetologist consultation in Nashik and prepare for it?
1. To book diabetologist in Nashik, contact RadhaKrishna Health clinic through its current listed phone number or booking channel. Confirm the doctor’s next available slot, consultation duration, fee, follow-up options and whether you can share reports before the visit.
2. Check the address before travelling: Shree Dwaraka Nagari, Adgaon Naka, Nashik, Maharashtra. If you cannot attend, ask the clinic to reschedule instead of leaving the appointment unused. Confirm whether teleconsultation or a caregiver-supported visit is available.
3. Carry recent HbA1c, fasting and post-meal glucose results, dated home-monitoring records, a continuous glucose monitor report if used, prescriptions, medicine and supplement lists with exact doses, insulin names and doses, kidney-function reports, lipid profile, blood-pressure readings, weight history and previous diabetes reports.
4. Ask the clinic whether fasting is required before arrival. Do not fast unless the planned test requires it, and take your usual medicines unless the clinician or testing instructions say otherwise. Bring your glucose meter, lancets and insulin records when reviewing technique, readings or device use could help.
Related service
Diabetology I provide diabetology consultation at RadhaKrishna Health Clinic in Nashik. View service → |
What happens during a diabetology consultation, and which numbers matter?
A diabetologist consultation in Nashik should review your pattern, not one isolated clinic reading. Discuss symptoms, weight change, meals, activity, medication adherence, insulin technique, low-glucose episodes and dated glucose trends. The clinician may check blood pressure, weight, pulse, feet, skin, pulses and loss of protective sensation with a 10-g monofilament plus vibration testing or reflexes.
Baseline risk assessment can include:
- Serum creatinine with estimated GFR, urine albumin-to-creatinine ratio and lipid profile
- Cardiovascular risk review and referral for a dilated retinal examination
- Foot inspection for ulcers, infection, footwear problems and circulation
| Measure | What it shows | How to interpret it |
|---|---|---|
| HbA1c | Average glucose over roughly the previous 2–3 months | Below 7% is a common starting target for many nonpregnant adults; frailty, major illness, recurrent hypoglycemia or treatment burden can justify another target |
| HbA1c timing | Longer-term treatment response | Check twice yearly when stable, or quarterly after treatment changes or when above target |
| HbA1c reliability | Red-blood-cell effects can distort the result | Anemia, hemoglobin variants, recent transfusion and advanced kidney disease may require glucose profiles or another measure |
| Kidney screening | Early diabetic kidney damage | Usually annually for type 2 diabetes; begin five years after type 1 onset |
The appointment may end with tests, treatment changes, education and a follow-up date. Do not change doses independently; ask the diabetologist in Nashik to explain every adjustment and its monitoring plan.
What guidance is needed for new, uncontrolled, pregnancy-related or insulin-treated diabetes?
The right questions depend on why your glucose is high. Use this comparison before a diabetology consultation in Nashik:
| Situation | Raise these details | Why it changes care |
|---|---|---|
| New diagnosis | Ask whether it is type 1, type 2, latent autoimmune, pancreatic or another secondary form; ask whether kidney, eye, nerve and foot screening is due | The diagnosis determines treatment and screening timing |
| Uncontrolled readings | Bring 7–14 days showing dates, meals, medicines, activity and symptoms | Treatment depends on cardiovascular disease, heart failure, chronic kidney disease, weight, hypoglycemia risk, cost and injection preference—not HbA1c alone |
| Pregnancy or planning pregnancy | State the pregnancy stage or plans immediately | Targets, medicines and retinal screening need earlier, more frequent review |
| Insulin or insulin-releasing medicine | Request a written low-glucose plan | You need clear actions for treatment and prevention |
| Older age or frailty | Discuss falls, cognition, frailty, meal regularity, kidney function and a safe target | An aggressive target can cause dangerous hypoglycemia |
If you have established cardiovascular disease or kidney disease, ask whether a medicine with proven cardiovascular or kidney benefit fits your treatment, even when HbA1c is near target. A diabetes specialist in Nashik should also review whether your readings reflect a different diabetes type.
Request written instructions covering when to take fast-acting glucose, when to recheck, and how a caregiver should use glucagon. Report pregnancy plans early, and never change insulin or other medicines without clinical advice.
Which mistakes can make diabetes follow-up less useful?
A follow-up becomes less useful when you alter the evidence before arriving. Do not stop insulin or other medicines to produce a better appointment reading, use someone else’s prescription, or bring isolated glucose values without dates, meal timing, symptoms and medication context.
| Mistake | Safer action | Why it matters |
|---|---|---|
| Stopping medicine before review | Take it as prescribed unless instructed otherwise | A falsely improved or worsened reading can lead to the wrong change |
| Treating low glucose with chocolate, a high-fat snack or an unmeasured drink | Follow the instructed fast-acting-carbohydrate and recheck plan | Fat slows glucose absorption and guessing the amount delays recovery |
| Giving food or drink to someone unconscious or unable to swallow | Do not force anything; use glucagon when available and contact emergency services | They can aspirate and severe hypoglycemia can cause seizure or death |
Before you book diabetologist in Nashik, verify the clinician’s registration and postgraduate training. Ask whether the service includes complication screening, nutrition and activity counselling, hypoglycemia education and follow-up.
Ask for written answers to these points:
- The next HbA1c date and your individual glucose targets
- Sick-day rules, medicine changes and when to seek urgent help
- Foot-care instructions and any required referrals
- When to repeat kidney tests, urine albumin, cholesterol and eye screening
A useful appointment ends with written instructions, not just a new prescription.
Frequently asked questions
When should you see a diabetologist instead of a general physician?
See a diabetologist for recurring high or low glucose, insulin treatment, difficult-to-control diabetes, complications, or uncertainty about the diagnosis. A general physician can assess an initial abnormal reading and routine type 2 diabetes follow-up.
How do you prepare for a diabetologist consultation in Nashik?
Carry your glucose meter or app records, medicine and insulin list, recent HbA1c and other reports, meal details, symptoms, and questions. Book a diabetology consultation in Nashik and ask whether fasting is needed for planned tests.
Which numbers matter during a diabetology consultation?
Discuss fasting glucose, post-meal glucose, HbA1c, hypoglycemia readings, blood pressure, kidney tests, urine albumin, cholesterol, weight, and glucose patterns rather than one isolated result.
What guidance is needed for new, uncontrolled, pregnancy-related, or insulin-treated diabetes?
New diabetes requires confirmation and classification. Uncontrolled diabetes needs a review of adherence, food, activity, medicines, infection, and complications. Pregnancy-related diabetes needs pregnancy-specific targets and obstetric coordination. Insulin-treated diabetes requires dose timing, injection technique, storage, sick-day rules, and hypoglycemia treatment.
What mistakes make diabetes follow-up less useful?
Do not stop medicines before the appointment without medical advice, bring incomplete glucose records, hide missed doses, test only when you feel unwell, or change insulin doses without a plan. Record readings with meal, medicine, exercise, and symptom details.
Keywords

